
Most bone grafting case studies stop at “the bone was rebuilt.” Case #7 goes one step further — the implant has already been placed into the new bone.**
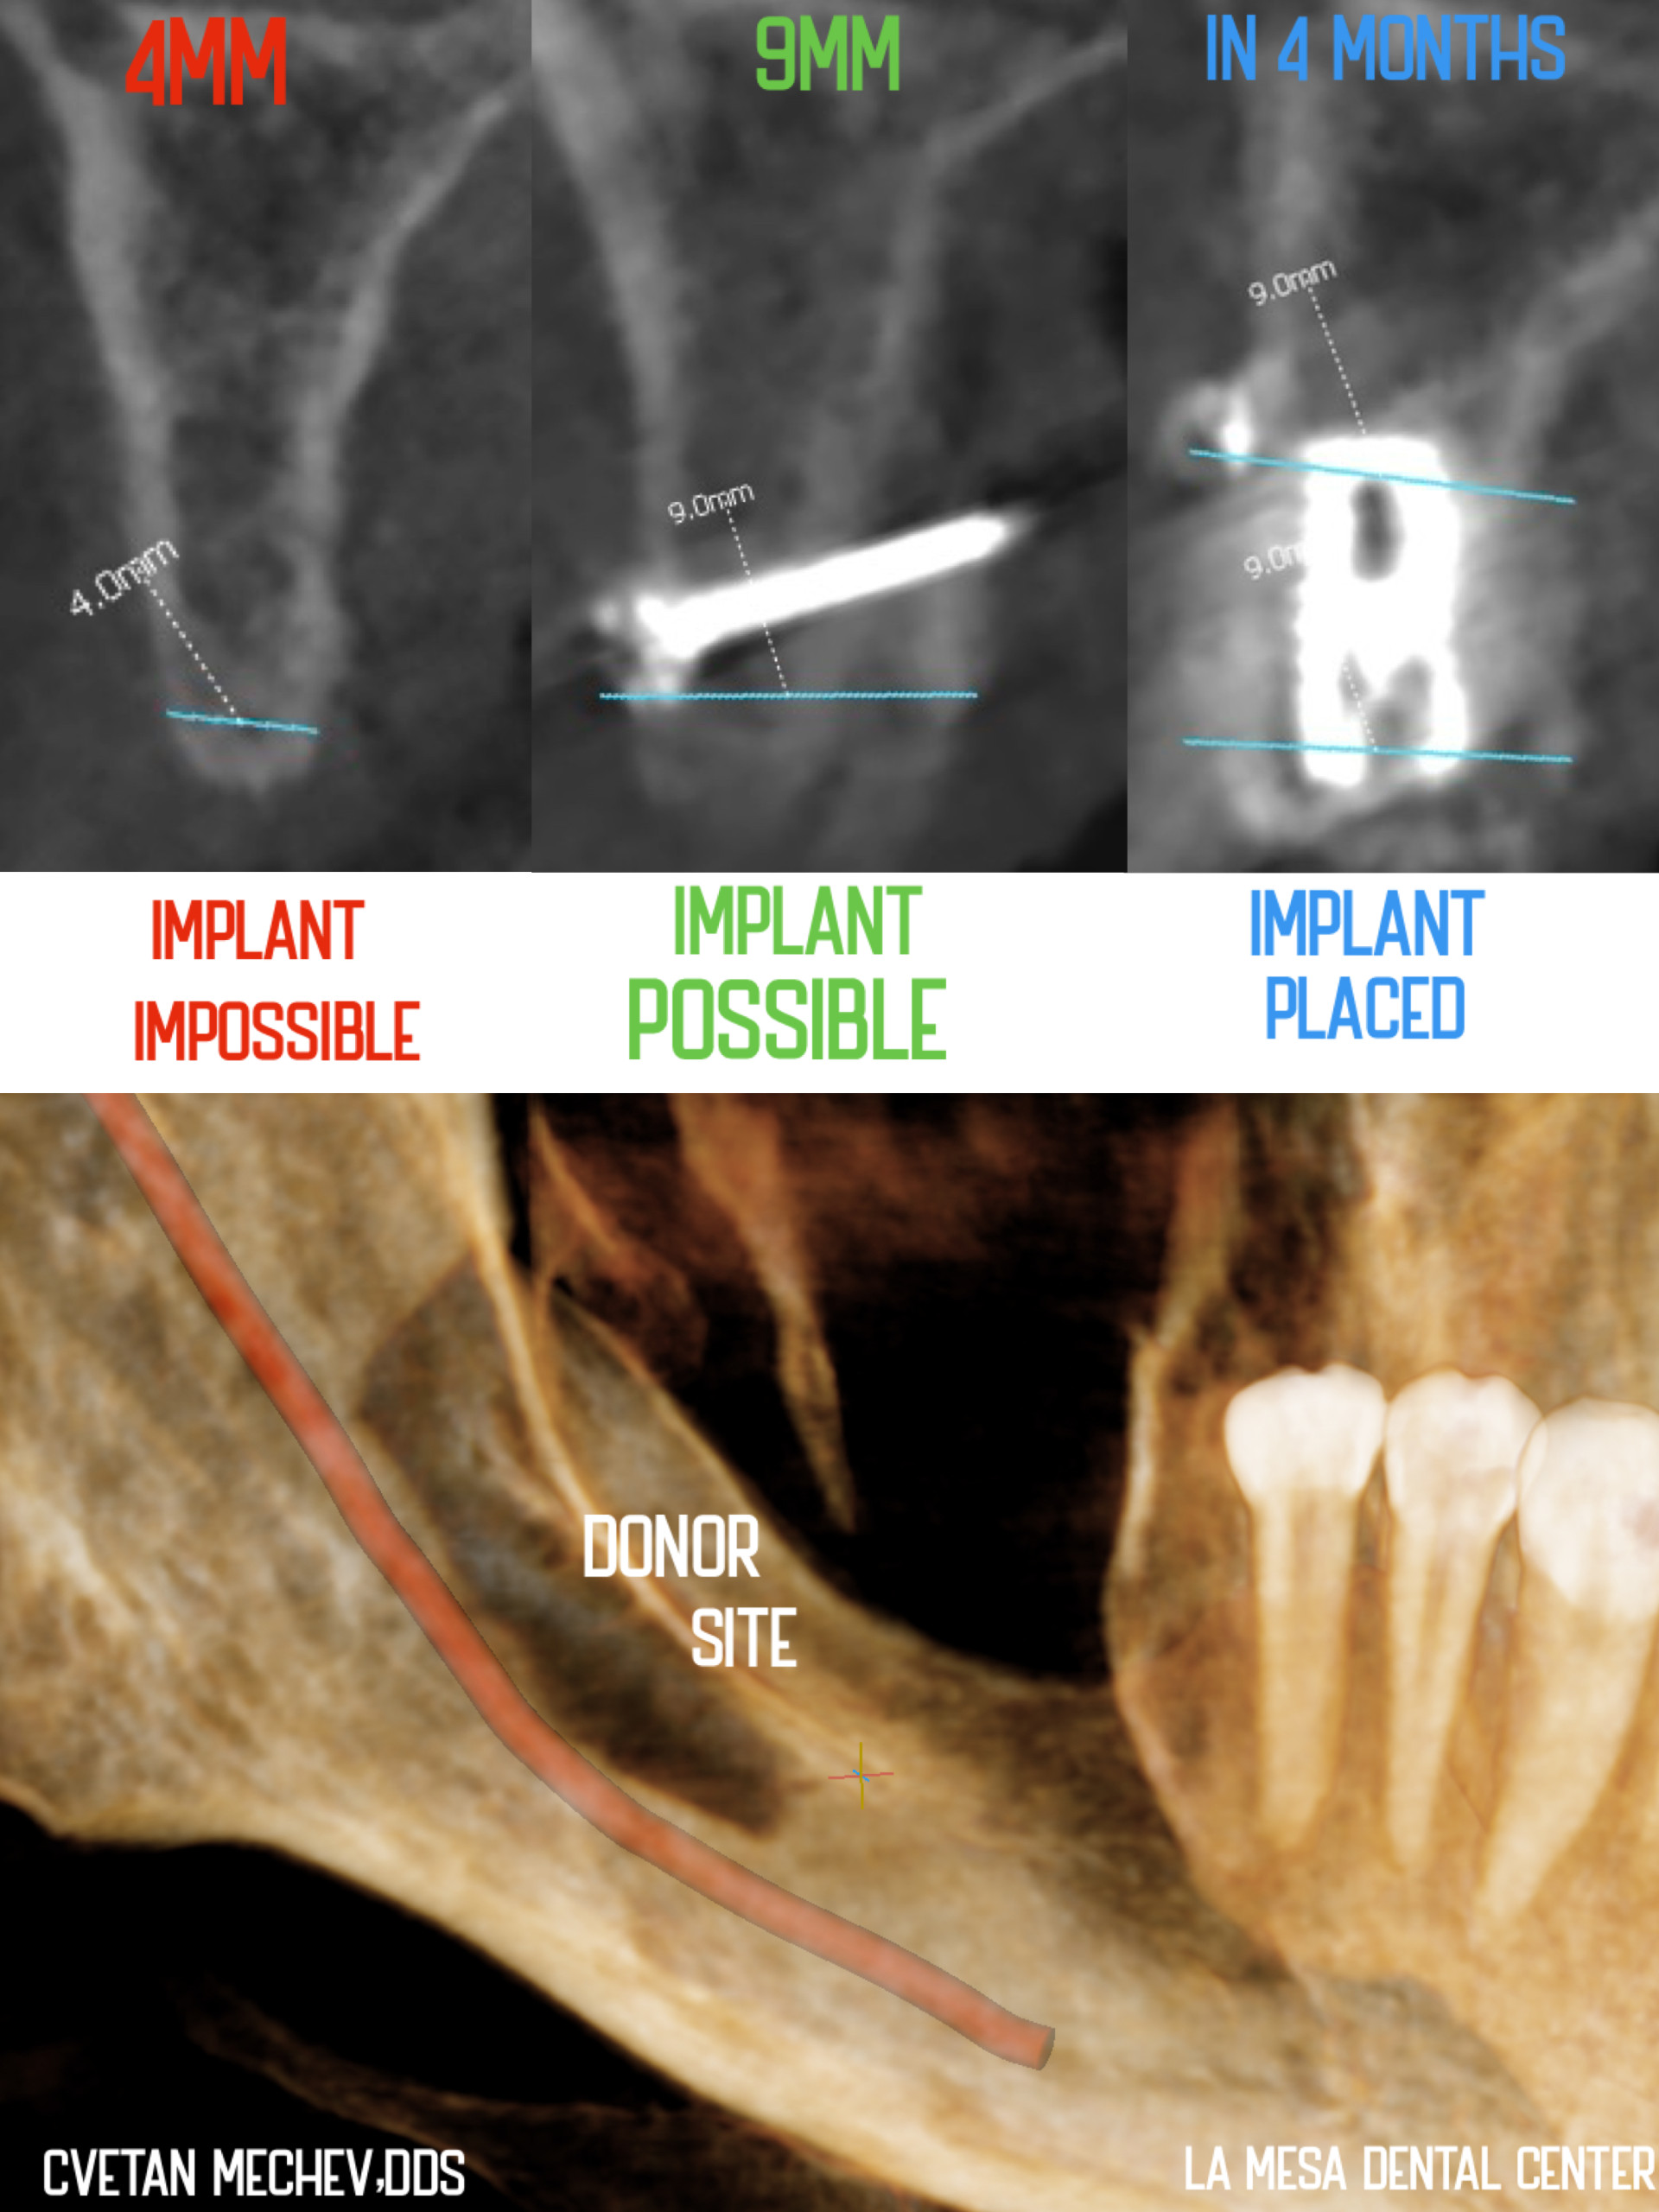
This is Case #7 in Dr. Cvetan Mechev’s large volume bone augmentation for dental implants series at La Mesa Dental Center. The CBCT images document the full journey in three stages: a jaw ridge too narrow for an implant, the same ridge rebuilt to meet the threshold, and the implant successfully placed into the new bone — all within 4 months.
The Problem: A Ridge That Made an Implant Impossible
When this patient first came to La Mesa Dental Center, CBCT imaging showed a jaw ridge measuring just **4 mm**. A standard dental implant needs a minimum of **7 mm** of bone width to be fully encased on all sides.
At 4 mm, placing an implant would have left it exposed beyond the bone margin — a direct path to bacterial infiltration, bone loss around the implant, and eventual failure. The first panel of the CBCT image puts it plainly: **Implant Impossible.**
Without bone augmentation, there was no safe path to an implant.
What the CBCT Images Show: Three Stages, One Story
The case documentation captures the entire treatment arc across three CBCT cross-sections:
- 4 mm — BEFORE augmentation — critical ridge deficiency confirmed; implant placement not possible
- 9 mm — AFTER augmentation — rebuilt ridge width confirmed; implant placement now possible
- 9 mm — AFTER implant placement — implant fully seated in the new bone, surrounded on all sides, confirmed at two independent measurement points
That third panel is the one that matters most. It confirms that the augmented bone was wide, dense, and stable enough to accept and hold a dental implant — the entire point of the procedure.
The Procedure: 100% Autogenous Bone Augmentation
Dr. Mechev rebuilt this patient’s ridge using 100% autogenous bone — bone taken directly from the patient’s own lower jaw, not from a synthetic substitute or donor tissue bank.
Autogenous bone is the gold standard for large-volume ridge augmentation because it is the only truly osteogenic graft material. It carries the patient’s own living bone cells, which actively generate new bone at the recipient site rather than simply providing a passive scaffold.
In this procedure:
- Bone was harvested from the donor site within the patient’s own lower jaw — the area behind the lower molars, where the wisdom teeth used to be
- The harvested bone was shaped and secured at the deficient recipient ridge
- Fixation screws held the graft in place while new bone formed around and through it
- After 4 months of healing, the augmented ridge was confirmed at 9 mm on CBCT — ready for implant placement
No synthetic material. No donor tissue. The patient’s own biology rebuilt the jaw.
Why This Case Is Different: The Implant Is Already In
Cases #9 and #10 in this series document the bone augmentation stage — the before and the rebuild. Case #7 and Case #8 show the complete picture.
The third CBCT panel shows the implant placed and fully seated in the newly built bone, with independent 9.0 mm measurements confirming the width around the implant. This is not a plan or a projection — it is a completed case, with the implant integrated into bone that did not exist four months prior.
This is what predictable, evidence-documented implant surgery looks like.
Why It Takes 4 Months — Not More, Not Less
Four months is Dr. Mechev’s standard healing window for horizontal bone augmentation before implant placement. During that time, the grafted bone undergoes a process called osseointegration — the new bone gradually fuses with the existing jaw structure and becomes dense enough to bear the load of an implant.
Rushing this stage risks placing an implant into bone that hasn’t fully matured and mineralized. Waiting too long provides no clinical benefit. The 4-month timeline is a documented, consistent standard in Dr. Mechev’s practice — confirmed by CBCT imaging at the follow-up appointment before any implant is placed.
Why 100% Autogenous Bone Gives the Most Predictable Results
There are several bone graft materials available in implant dentistry: synthetic substitutes, freeze-dried donor bone (allograft), animal-derived materials (xenograft), and autogenous bone. Each has a role.
For cases where the ridge needs significant rebuilding — like this one, where 5 mm of width had to be created — autogenous bone offers the most predictable outcome because:
- It carries the patient’s own living bone cells — no rejection risk
- It actively generates new bone, not just a scaffold for other tissue to fill
- It integrates faster and more densely than synthetic alternatives
- The resulting bone is the patient’s own — indistinguishable from native jaw bone on imaging
The fixation screws visible in the CBCT hold the graft block/plate precisely in position while the bone matures. This stability is critical — any movement during healing can disrupt the integration process.
Horizontal vs. Vertical Bone Augmentation
This case addresses horizontal bone loss — the ridge was too narrow, not too short. For comparison:
Horizontal augmentation rebuilds the width of the jaw ridge — the dimension that determines whether an implant can be fully enclosed in bone from front to back.
Vertical augmentation rebuilds the height of the jaw ridge — the dimension that determines how deep an implant can be seated.
In Case #7, the deficit was entirely in the horizontal dimension — 4 mm where 7 mm minimum was needed, with the final result reaching 9 mm.
For a vertical augmentation case, see Case #9 — a 6 mm vertical gain using the Safecut technique. For other horizontal cases, see Case #10 — a 5 mm horizontal augmentation, and Case #8 — a 2.5 mm to 7 mm horizontal rebuild.
Who Needs Horizontal Bone Augmentation Before an Implant?
Horizontal ridge loss is one of the most common reasons patients are told they cannot have a dental implant. The bone that held the tooth’s root starts to shrink almost immediately after an extraction, and without stimulation from a root, it narrows progressively over months and years.
You may be a candidate for horizontal bone augmentation if:
- A dentist told you your jaw is “too thin” for an implant
- You lost a tooth years ago and never had it replaced
- Previous trauma or infection caused localized bone loss
- A CBCT scan shows a ridge width below 7 mm at the planned implant site
Many patients who are told implants are not possible can have the bone rebuilt and an implant placed — just like this patient.
Dr. Mechev’s Approach: Computer-Guided, CBCT-Documented, All In-House
Every case at La Mesa Dental Center starts with a CBCT scan — a full 3D map of the jaw that confirms exact bone dimensions before any surgical planning begins. No guessing. No estimating.
Dr. Cvetan Mechev, DDS has been practicing dentistry for 26 years. He trained internationally in Dubai (UAE), London (UK), Padua (Italy), and Budapest (Hungary) to learn advanced bone grafting techniques. He is the only dentist in San Diego and California who trained twice in Padua under Dr. Luca De Stavola, learning the Safecut method protocol — a computer-guided way to take and harvest bone from one part of the jaw and use it to rebuild another area before placing a dental implant. This training covers both widening a thin jaw (horizontal grafting) and building up a short jaw (vertical grafting).
He performs the full scope of ridge augmentation and implant procedures in-house at La Mesa Dental Center — from CBCT planning through bone augmentation, healing, implant placement, and final crown:
- Horizontal bone ridge augmentation
- Vertical bone ridge augmentation
- Bone graft for dental implants
- Guided tissue and bone regeneration
- Sinus lift for dental implants
- Dental implants
Serving San Diego, La Mesa, El Cajon, Spring Valley, and Southern California
La Mesa Dental Center is located at 8334 University Ave, La Mesa, CA 91942, serving patients from La Mesa, El Cajon, Spring Valley, Lemon Grove, San Diego, and Southern California.
If you’ve been told your jaw is too thin for a dental implant, a CBCT scan and consultation with Dr. Mechev will show you what is actually possible.
Call (619) 337-2424 or request an appointment online.
Frequently Asked Questions
How long does it take to get a dental implant after bone grafting?
In Dr. Mechev’s practice, the standard healing time after horizontal bone augmentation is 4 months. After that, a CBCT scan confirms the bone is ready, and the implant is placed.
Can the same dentist do the bone graft and the implant?
Yes. At La Mesa Dental Center, Dr. Mechev handles the entire process — CBCT scanning, bone augmentation, healing follow-up, implant placement, and final implant crown — without referrals to other offices.
How much bone do I need for a dental implant?
A standard implant requires a minimum of 7 mm of bone width to be fully enclosed. This patient started at 4 mm and was successfully brought to 9 mm through horizontal bone augmentation.
Why does Dr. Mechev use the patient’s own bone instead of synthetic material?
Autogenous bone is the only graft material that carries living bone cells and actively builds new bone. For large-volume deficiencies, it gives the most predictable, durable result.
What is a CBCT scan and why is it used?
A CBCT scan gives Dr. Mechev a precise 3D map of the patient’s jawbone before any surgery. It confirms exact bone dimensions and documents the result after healing. Every bone grafting case at La Mesa Dental Center is planned and confirmed with CBCT imaging.


